
Testosterone vs. Enclomiphene for Men: Which Hormone Strategy Actually Works in 2026?
For men with confirmed low testosterone, the core clinical question in 2026 is no longer simply whether to treat — it's which axis to target. Exogenous testosterone replacement restores circulating levels directly but suppresses the body's own production machinery; enclomiphene citrate works upstream, coaxing the hypothalamic-pituitary axis to generate more testosterone endogenously, with the critical side effect of preserving — or even improving — sperm output.
That distinction matters far more than most men realize when they first walk into a clinic or log onto a telehealth platform. Both approaches can move total testosterone from hypogonadal territory into the normal range. What diverges is everything downstream: gonadotropin levels, intratesticular testosterone, semen parameters, long-term testicular function, and regulatory status. Understanding those differences is the difference between a treatment plan that fits your life and one that creates new problems while solving the original one.
Starting from
$99.99/mo
Free consultation

4.2 AHF · 4.2 Trustpilot
Affordable multi-modality TRT with board-certified physicians + at-home labs + coaching — broader access than mass-market without the premium-concierge tier.
Get Started FreeWhat the Evidence Actually Says About Male Hypogonadism
Male hypogonadism is not a single condition. The Endocrine Society Clinical Practice Guidelines on male hypogonadism draw a sharp line between primary hypogonadism — where the testes themselves are failing, LH and FSH are elevated, and exogenous replacement is typically the only viable option — and secondary or functional hypogonadism, where the testes are intact but central drive is suppressed, often by obesity, metabolic syndrome, chronic illness, or sleep disruption [11]. That second phenotype is far more prevalent in the real-world patient population showing up at men's health clinics today, and it is precisely the population for whom enclomiphene is most relevant.
The Endocrine Society's diagnostic threshold requires both symptoms consistent with testosterone deficiency — decreased libido, erectile dysfunction, fatigue, mood changes, reduced muscle mass — and two separate morning fasting total testosterone measurements below the normal range, confirmed with accurate assays [11][13]. Free testosterone should be assessed when sex hormone-binding globulin is abnormal or total testosterone lands near the lower limit of normal. This careful two-step confirmation requirement exists specifically to prevent overtreating men whose symptoms reflect aging, lifestyle, or comorbidities rather than true hypogonadism.
The epidemiological backdrop matters here. Travison et al. (2007), published in the Journal of Clinical Endocrinology & Metabolism, documented a population-level decline in male testosterone across successive birth cohorts — independent of aging — suggesting that some of what clinicians see today reflects secular trends rather than individual pathology [12]. That doesn't mean symptomatic men shouldn't be treated; it means the diagnostic bar should be cleared before committing a man to a lifetime of exogenous hormones or long-term SERM therapy.
For men who are on the fence about whether their symptoms warrant treatment at all, the guide to distinguishing low testosterone from normal aging is a useful starting point before any clinical conversation.

How Testosterone Therapy Works — and What It Costs the Body
Testosterone replacement therapy works by bypassing the hypothalamic-pituitary-gonadal (HPG) axis entirely. Injectable formulations like Depo-Testosterone (testosterone cypionate) at 100–200 mg weekly or every two weeks, transdermal gels like AndroGel, and newer options like Xyosted (subcutaneous testosterone enanthate auto-injector) all deliver exogenous androgen directly into circulation [16]. The body reads elevated circulating testosterone and estradiol as a signal to reduce GnRH, LH, and FSH — which is exactly what it's designed to do under normal negative feedback conditions. The result is suppressed endogenous production.
That suppression is not a theoretical concern. In the randomized phase IIb trial comparing topical testosterone gel to enclomiphene, men receiving gel saw LH drop by approximately 4.4 mIU/mL and FSH drop by 2.4 mIU/mL within three months. More than half — 54% — became oligospermic. In the enclomiphene arms, both gonadotropins rose and sperm concentration was statistically indistinguishable from placebo [6]. The Testosterone Trials (TTrials), the NIH-funded seven-arm study of testosterone therapy in older men, confirmed that TRT reliably raises serum testosterone and improves sexual function, bone density, and anemia in confirmed hypogonadism — but those trials enrolled older men not seeking fertility, which limits their applicability to younger patients [11].
Cardiovascular safety, long the biggest unanswered question in TRT, now has a more definitive answer. The TRAVERSE trial — a postmarketing safety study of AndroGel 1.62% mandated by the FDA — enrolled more than 5,200 hypogonadal men and tracked major adverse cardiovascular events. The result: MACE in 7.0% of the testosterone group versus 7.3% in placebo, with no meaningful signal of elevated cardiovascular risk [15]. That finding has substantially changed the risk conversation, though the Endocrine Society still recommends individualized treatment decisions and continued monitoring, particularly in older men with pre-existing cardiovascular disease [11][13].
On cost, injectable testosterone cypionate remains one of the most economical treatment options in men's health. A 10 mL vial at 200 mg/mL typically runs $40–90 at retail without insurance; at 100 mg per week, that vial covers roughly 20 weeks, translating to about $8–18 per month in medication costs [20]. Gels and auto-injectors carry higher price tags — branded formulations can run $300–600 monthly without insurance — though generic options have compressed that gap. Men exploring the full cost landscape can find a current breakdown through the hormone optimization treatment hub.
Readers in communities like r/Biohackers and r/menshealth consistently describe TRT as the "nuclear option" — effective and fast, but perceived as a one-way door for natural production. The dominant concern isn't cardiovascular risk; it's the sense that going on testosterone means staying on it indefinitely, or facing a protracted recovery period if they stop.
How Enclomiphene Works — and Why the Mechanism Matters
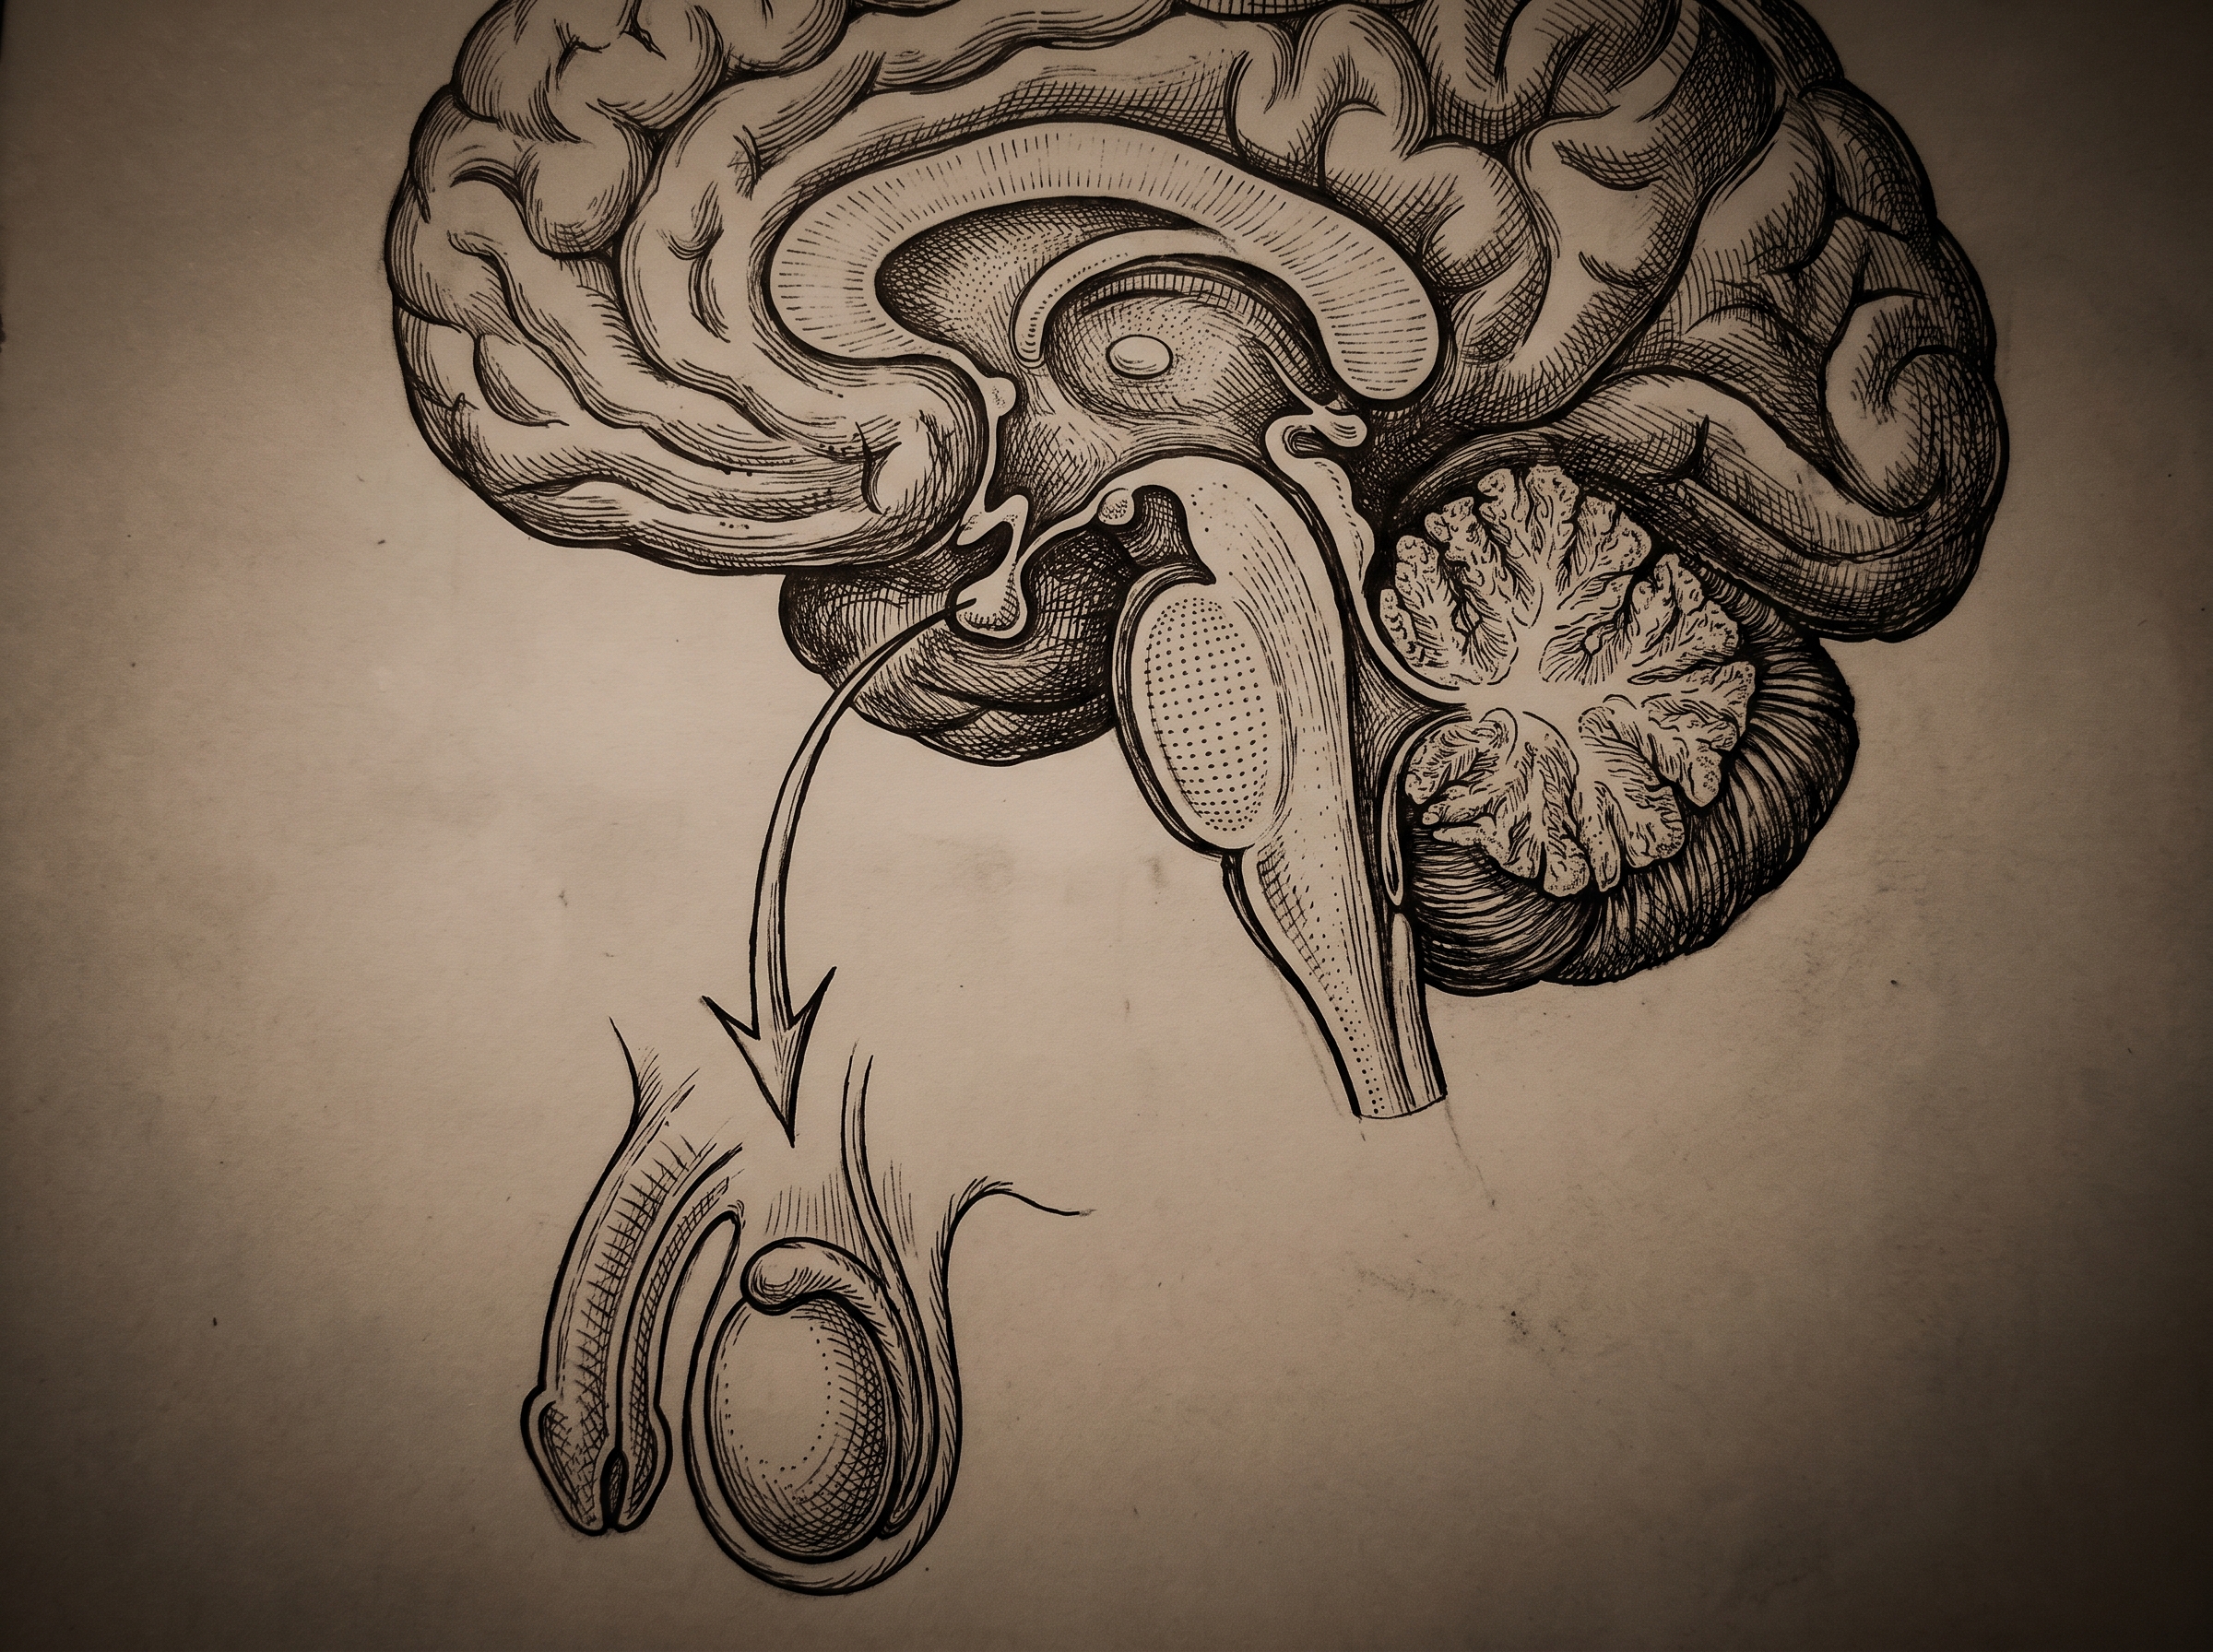
Enclomiphene citrate is the trans-isomer of clomiphene, a selective estrogen receptor modulator (SERM) that has been used for decades in female fertility medicine. In men, its target is hypothalamic estrogen receptors. By competitively blocking estrogen's negative feedback at the hypothalamus, enclomiphene increases GnRH pulse frequency, which drives LH and FSH release from the pituitary, which in turn stimulates Leydig cell testosterone synthesis in the testes [1][5]. The entire axis stays intact and active — the treatment is stimulatory, not substitutive.
The clinical implications of that distinction are significant. Because intratesticular testosterone concentrations are many times higher than circulating levels, and because spermatogenesis depends on that intratesticular environment, enclomiphene raises the very testosterone pool that exogenous TRT depletes. In the pivotal phase II randomized trial, men receiving enclomiphene 25 mg daily reached a mean total testosterone of 604 ± 160 ng/dL at six weeks — comparable to topical testosterone gel's 500 ± 278 ng/dL — but their LH and FSH rose rather than fell, and their sperm parameters remained stable [1]. The study authors concluded that enclomiphene reverses both hallmarks of secondary hypogonadism: low testosterone and inappropriately low (or low-normal) LH [1].
A separate proof-of-concept trial specifically enrolled men who had been on topical testosterone and wanted to transition off. After cessation of gel, average morning testosterone fell to 165 ng/dL. Enclomiphene restored and maintained levels — 525 ± 256 ng/dL at six months — while increasing sperm counts in all treated men to concentrations between 75 and 334 × 10⁶/mL. The gel group, by contrast, failed to push sperm counts above 20 × 10⁶/mL in most participants [10]. For men who want to preserve or recover fertility, this is not a marginal difference.
The broader meta-analytic data, drawn from a systematic review of SERM trials in functional hypogonadism covering 819 patients across ten trials, found that clomiphene and enclomiphene increased total testosterone by a weighted mean difference of 273.76 ng/dL versus placebo, with LH rising by 4.66 IU/L and FSH by 4.59 IU/L [2][3]. Total testosterone outcomes were not statistically different from testosterone gel groups — but LH, FSH, and sperm concentration parameters were significantly better with SERMs [2][3]. The fertility advantage is not subtle.
Men exploring enclomiphene in online communities — particularly r/Biohackers and r/menshealth discussions — often describe it as a way to "keep the engine running." The appeal is the possibility of raising lab numbers without fully suppressing endogenous production. A common reported frustration, however, is that symptom relief is more variable than the numbers suggest: plenty of users report testosterone levels climbing into the 500–700 ng/dL range while still feeling flat, with energy and libido improvements that don't fully match the biochemical improvement.
For men weighing enclomiphene against Clomid (clomiphene citrate, which contains both the active trans-isomer and the less desirable cis-isomer), enclomiphene's theoretical advantage is fewer estrogenic agonist effects — though direct comparative trial data remain limited [5][18].
Head-to-Head: Efficacy, Fertility, and Safety Trade-offs
On the primary efficacy endpoint — raising serum total testosterone into the normal range — testosterone therapy and enclomiphene perform comparably in men with secondary hypogonadism. Multiple phase II and phase III trials, plus meta-analyses, consistently show both approaches moving total testosterone to the 500–600 ng/dL range after weeks to months of treatment, with no statistically significant between-group difference in that single endpoint [1][2][3][5][6]. If all you measure is a morning total testosterone number, the two treatments look nearly identical.
Where they diverge sharply is on everything the total testosterone number doesn't capture. Testosterone therapy suppresses LH and FSH in nearly every patient. Enclomiphene raises them. Testosterone therapy produces oligospermia in more than half of treated men within three months. Enclomiphene produces oligospermia rates no different from placebo [6]. A separate systematic review of clomiphene in men with hypogonadism — 19 studies, 1,642 patients — found that clomiphene increased total testosterone, free testosterone, LH, FSH, SHBG, and estradiol, with clinical symptom improvements and fewer than 10% of patients reporting side effects, and no serious adverse events documented [7][8]. Enclomiphene, as the more purely anti-estrogenic isomer, is expected to share these benefits with potentially less estrogenic agonist activity.
Safety profiles differ in character rather than severity. TRT's established risks include erythrocytosis (elevated hematocrit), testicular atrophy with prolonged use, and — as noted — transient infertility that may take months to reverse after discontinuation. The TRAVERSE data have largely resolved the acute cardiovascular concern for appropriately selected patients [15]. Enclomiphene's side effect profile from trials is mild: occasional visual disturbances (a class effect of SERMs), mood variability, and mild gastrointestinal symptoms; serious adverse events in randomized trials were rare and mostly limited to the 25 mg dose [6]. The vision-related concern — which reflects estrogen receptor activity in the retina — is something online communities flag consistently, with some users reporting transient blurry vision at higher doses, reinforcing the case for the 12.5 mg starting dose.
One population-specific consideration: the Endocrine Society guidelines explicitly recommend against initiating TRT in men who are actively trying to conceive, suggesting SERMs, gonadotropins, or other fertility-preserving approaches instead [11][13]. Enclomiphene fits squarely in that recommended category for secondary hypogonadism. For primary hypogonadism — elevated LH and FSH, poor testicular reserve — enclomiphene has no role; the testes cannot respond to additional gonadotropin stimulation, and exogenous testosterone is the appropriate management.
Men in Illinois considering in-person evaluation can find experienced clinicians through Chicagoland Men's Health - Low Testosterone Replacement Therapy, and Florida-based men have several options including Vitality Health SFL and TRT Nation.
The Regulatory Gap: Why Enclomiphene Isn't at Your Pharmacy
This is where the comparison becomes practically complicated. Testosterone — in its various branded and generic injectable and topical forms — is FDA-approved, broadly covered by insurance for confirmed hypogonadism, and available at every pharmacy. Depo-Testosterone, Aveed (testosterone undecanoate for injection), Xyosted, AndroGel, Axiron — these are all navigated through standard prescribing channels [16]. Enclomiphene is not.
Despite completing phase III trials that demonstrated efficacy comparable to testosterone gel with superior fertility preservation, enclomiphene (marketed under the investigational name Androxal by Repros Therapeutics) did not receive FDA approval for male hypogonadism. The agency's primary concern at the time of review was that testosterone was the established standard of care and that the applicant had not demonstrated a compelling advantage sufficient to support approval. As of September 2026, enclomiphene for men remains available only through compounding pharmacies — meaning it is not covered by most insurance plans, is not subject to standard pharmaceutical manufacturing quality controls, and operates in a regulatory gray zone [19].
That has real implications. Compounded enclomiphene typically runs $50–150 per month depending on dose and pharmacy, which is manageable but not trivial for a long-term treatment. The quality and consistency of compounded formulations vary, and patients should verify that their pharmacy holds appropriate accreditation. The telehealth boom has made enclomiphene more accessible — numerous platforms now prescribe it off-label for secondary hypogonadism — but the lack of FDA approval means that the clinical evidence base, while solid for the investigational compound, doesn't map perfectly onto what a patient is actually receiving from a specific compounding pharmacy.
Men working with telehealth providers should confirm that their prescriber is evaluating them against the Endocrine Society's diagnostic criteria, not just a single low testosterone reading. Platforms like PeterMD structure their evaluation process around proper clinical workup, which matters when the treatment decision involves a compound outside the standard approval pathway.
The regulatory gap also shapes the clinical conversation around long-term monitoring. TRT patients have decades of follow-up data, established protocols for hematocrit monitoring, and clear re-testing intervals. Enclomiphene's long-term data beyond six to twelve months of treatment is thinner, and monitoring protocols are less standardized across prescribing practices. That's not a reason to avoid it — the mechanistic rationale and short-to-medium-term trial data are compelling — but it is a reason to work with a clinician who is genuinely tracking outcomes rather than simply refilling a prescription.
Who Should Choose Which: A Clinical Decision Framework
The choice between testosterone therapy and enclomiphene is not primarily about which one raises testosterone more effectively — both do, comparably. It's about matching the mechanism to the patient's biology and priorities.
Exogenous testosterone — whether injectable Depo-Testosterone, a transdermal gel like AndroGel, or a subcutaneous formulation like Xyosted — is the appropriate first-line choice for men with primary hypogonadism, older men who have completed their families, men with confirmed central hypogonadism where the axis cannot be adequately stimulated, and men whose symptoms are severe enough to require the most reliable and fastest-acting option [11][13]. The Bhasin et al. 2018 analysis in the New England Journal of Medicine, synthesizing results from the Testosterone Trials, demonstrated meaningful improvements in sexual function, bone density, and anemia in older hypogonadal men — a population for whom fertility preservation is not the relevant clinical endpoint. TRT is also the right choice for men who have already tried SERMs without adequate symptom response.
Enclomiphene is the stronger argument for men under 45 with secondary or functional hypogonadism, men who are actively trying to conceive or planning to in the next few years, men who want to preserve endogenous axis function, and men who want to avoid the commitment of indefinite exogenous hormone replacement. The JCEM-published data — including the phase IIb trial results — show that enclomiphene achieves comparable testosterone normalization with superior gonadotropin and sperm outcomes in exactly this phenotype [5][6]. Clomid (clomiphene citrate) is a lower-cost, FDA-approved alternative that some clinicians use off-label when enclomiphene is unavailable, with the caveat that the cis-isomer component may add estrogenic agonist effects.
A third path worth acknowledging: some clinicians use enclomiphene as a bridge or diagnostic tool — prescribing it for three to six months to confirm that the HPG axis is responsive before committing to long-term TRT. A robust testosterone response to enclomiphene confirms secondary hypogonadism and opens the door to lifestyle interventions (weight loss, sleep optimization, alcohol reduction) that may sustain testosterone without pharmacotherapy. Readers interested in the sleep angle specifically will find relevant data in the analysis of how TRT affects sleep.
For men in Nevada, MODERN WELLNESS CLINIC provides structured hormone evaluations, and men in Florida can also explore Aspire Rejuvenation Clinic - Orlando or Overtime Men's Health for in-person consultations. The broader provider comparison hub for HRT covers telehealth options across all major platforms.
The estrogen management question also plays differently across the two approaches. TRT increases circulating estradiol through peripheral aromatization, and many practitioners reflexively prescribe aromatase inhibitors — often unnecessarily. Enclomiphene also raises estradiol modestly (by stimulating more testosterone production, which then aromatizes), but this is often less pronounced. Men on TRT who are worried about estradiol management should review the evidence before requesting an AI; the evidence-based reframing of estrogen on TRT is worth reading before that conversation with a prescriber.

Practical Considerations: Monitoring, Cost, and Long-Term Management
Both treatments require ongoing monitoring, but the specific markers differ. Men on testosterone therapy need periodic hematocrit checks (erythrocytosis is the most common clinically significant adverse effect), PSA monitoring in men over 40, and testosterone level testing to confirm appropriate dosing without supratherapeutic peaks [11][13]. Injectable formulations may require dose or frequency adjustments to manage trough symptoms. TRT's impact on sleep apnea — which it can worsen — is underappreciated; men with existing sleep-disordered breathing warrant specific screening.
Men on enclomiphene need total testosterone, LH, FSH, and estradiol monitoring — the last because SERM therapy raises estradiol alongside testosterone, and persistently elevated estradiol can cause gynecomastia or mood instability in some patients. Semen analysis every three to six months is appropriate for men actively trying to conceive. The 12.5 mg dose is generally the recommended starting point, with escalation to 25 mg if the hormonal response is inadequate at three months. Community reports suggest that some men do well on even lower doses — 6.25 mg — particularly those who respond robustly to central stimulation, though this falls below the trial-tested range.
Cost matters in long-term adherence. Injectable testosterone cypionate remains the most affordable option by a wide margin, often under $20/month for generic formulations [20]. Branded gels and auto-injectors can run $300–600/month without insurance. Compounded enclomiphene typically falls in the $50–150/month range, which is competitive with branded TRT formulations but higher than generic injectable testosterone. Insurance covers TRT for documented hypogonadism far more reliably than compounded enclomiphene, which affects real-world cost for most patients. Men comparing full cost of care — including monitoring labs, provider fees, and medication — can find a structured breakdown for TRT providers by location in Florida or other states.
For men in California, the California TRT provider directory includes both telehealth and in-person options with verified credentials. Men seeking clinic-based care in Florida can also evaluate The Health Carpenter Direct Primary Care & Aesthetics in Orlando and BioDesign Men's Clinic of Tampa in Tampa as examples of structured men's health programs that address both the diagnostic and monitoring components systematically.
Frequently Asked Questions
Is enclomiphene as effective as testosterone therapy for raising testosterone levels?
In men with secondary or functional hypogonadism, enclomiphene raises total testosterone to the normal range — typically 500–600 ng/dL — with efficacy statistically comparable to topical testosterone gel in multiple phase II and phase III randomized trials [1][5][6]. The key difference is mechanism: enclomiphene achieves this by stimulating endogenous LH and FSH, while testosterone therapy delivers exogenous androgen directly. For the single endpoint of serum total testosterone, the two approaches perform similarly; for fertility, gonadotropin levels, and long-term axis preservation, enclomiphene is meaningfully superior in secondary hypogonadism.
Can enclomiphene preserve fertility while treating low testosterone?
Yes — this is enclomiphene's primary clinical advantage over exogenous testosterone. In the pivotal phase IIb randomized trial, more than half of men receiving topical testosterone gel became oligospermic within three months, while men receiving enclomiphene showed sperm concentration rates no different from placebo [6]. A separate trial found that enclomiphene restored sperm counts in all treated men transitioning off testosterone gel, reaching concentrations between 75 and 334 × 10⁶/mL at six months [10]. The Endocrine Society Clinical Practice Guidelines specifically recommend against initiating TRT in men actively trying to conceive, making enclomiphene the guideline-consistent choice for this population [11].
What are the main side effects of enclomiphene compared to TRT?
Enclomiphene's most commonly reported side effects in clinical trials are mild: occasional visual disturbances (a class effect of SERMs reflecting estrogen receptor activity in the retina), mood variability, and minor gastrointestinal symptoms, with serious adverse events rare [6]. TRT carries a different risk profile: erythrocytosis (elevated hematocrit), suppression of endogenous production and testicular atrophy with prolonged use, potential worsening of sleep apnea, and transient infertility that may take months to reverse after discontinuation. The TRAVERSE trial found no meaningful difference in major cardiovascular events between testosterone and placebo in appropriately selected patients [15], but individualized risk assessment remains essential.
Is enclomiphene FDA-approved, and can I get it through insurance?
Enclomiphene is not FDA-approved for male hypogonadism as of September 2026. Despite completing phase III trials, the compound (investigated as Androxal) did not receive approval, and it is currently available only through compounding pharmacies in the United States [19]. That means most insurance plans do not cover it, and patients pay out of pocket — typically $50–150 per month depending on dose and pharmacy. Exogenous testosterone formulations including Depo-Testosterone, AndroGel, Xyosted, and Aveed are FDA-approved and covered by insurance for confirmed hypogonadism, making them the default option in insurance-driven clinical settings. Men pursuing enclomiphene should work with a prescriber who applies the same rigorous diagnostic criteria the Endocrine Society requires for TRT [11][13].
How do I know whether I have primary or secondary hypogonadism, and why does it matter for this decision?
Primary hypogonadism involves testicular failure — the testes cannot produce adequate testosterone even when properly stimulated. LH and FSH are elevated as the pituitary tries to compensate. Secondary (or functional) hypogonadism involves suppressed central drive — the testes are capable but the hypothalamic-pituitary signal is inadequate — and LH and FSH are low or inappropriately normal. This distinction is critical because enclomiphene works by amplifying that central signal; it has no mechanism of action in primary hypogonadism where the testes cannot respond [11][13]. A proper workup — including two morning total testosterone measurements, LH, FSH, and evaluation of comorbidities — determines which pattern applies. Men who are unsure about their diagnosis should seek evaluation before starting either treatment, and a men's health TRT provider near them can facilitate the appropriate workup.
Sources
[1] Kim et al. — Enclomiphene Phase II Randomized Trial (PMC4155868)
[2] SciELO Press Release — Clomiphene and Enclomiphene Meta-Analysis
[3] PubMed — SERM Meta-Analysis in Functional Hypogonadism (41066380)
[5] Wiehle et al. — Enclomiphene Phase IIb/III (PMC5009465)
[6] MedCentral — Enclomiphene Phase IIb Sperm/Hormone Outcomes
[7] Andrologia — Clomiphene Meta-Analysis (andr.13146)
[8] Andrologia — Clomiphene Meta-Analysis Full Text
[10] Sciencedirect — Enclomiphene as Testosterone Gel Substitute
[11] Endocrine Society — Clinical Practice Guidelines on Male Hypogonadism
[12] Travison et al. — Population-Level Decline in Serum Testosterone (JCEM, PMID 17062768)
[13] JCEM — Testosterone Therapy in Men with Hypogonadism CPG
[15] FDA — TRAVERSE Trial / Testosterone Postmarket Safety Information
[16] FDA Label — Testosterone Cypionate (accessdata)
[18] MDPI Pharmaceuticals — SERM Review in Male Hypogonadism
[19] HealthRx — Accessing Enclomiphene / Compounding Overview
Alpha Health Finder Editorial Team
Editorial Team
The Alpha Health Finder editorial team researches and writes evidence-based men's health content. Articles are grounded in cited primary sources and reviewed against a fixed editorial standard before publication. We are a research and directory team — not your prescribing clinicians.
Looking for an online provider?
Find a qualified online provider — compare options vetted and reviewed by Alpha Health Finder.



