
TRT vs. Enclomiphene for Fertility: Which Hormone Strategy Should Men Choose in 2026?
For men with hypogonadism who want to father children, the choice between conventional testosterone replacement and enclomiphene is not a matter of preference — it is a matter of biology. Standard exogenous testosterone reliably shuts down sperm production; enclomiphene works through an entirely different mechanism that preserves and often improves it.
Understanding why that split exists requires a short detour into HPG-axis physiology, followed by a hard look at what the clinical trials actually show. The evidence here is strong enough to take a clear position: if fertility is on the table now or in the foreseeable future, conventional TRT is the wrong first-line tool, and the Endocrine Society Clinical Practice Guidelines on male hypogonadism say as much.
Starting from
$1.60
Free consultation

3.8 AHF · 3.2 Trustpilot
Among the lowest sildenafil prices in telehealth — fits low-frequency users on tight budgets, with persistent customer-service watch points.
Get Started FreeWhy Exogenous Testosterone Suppresses Fertility
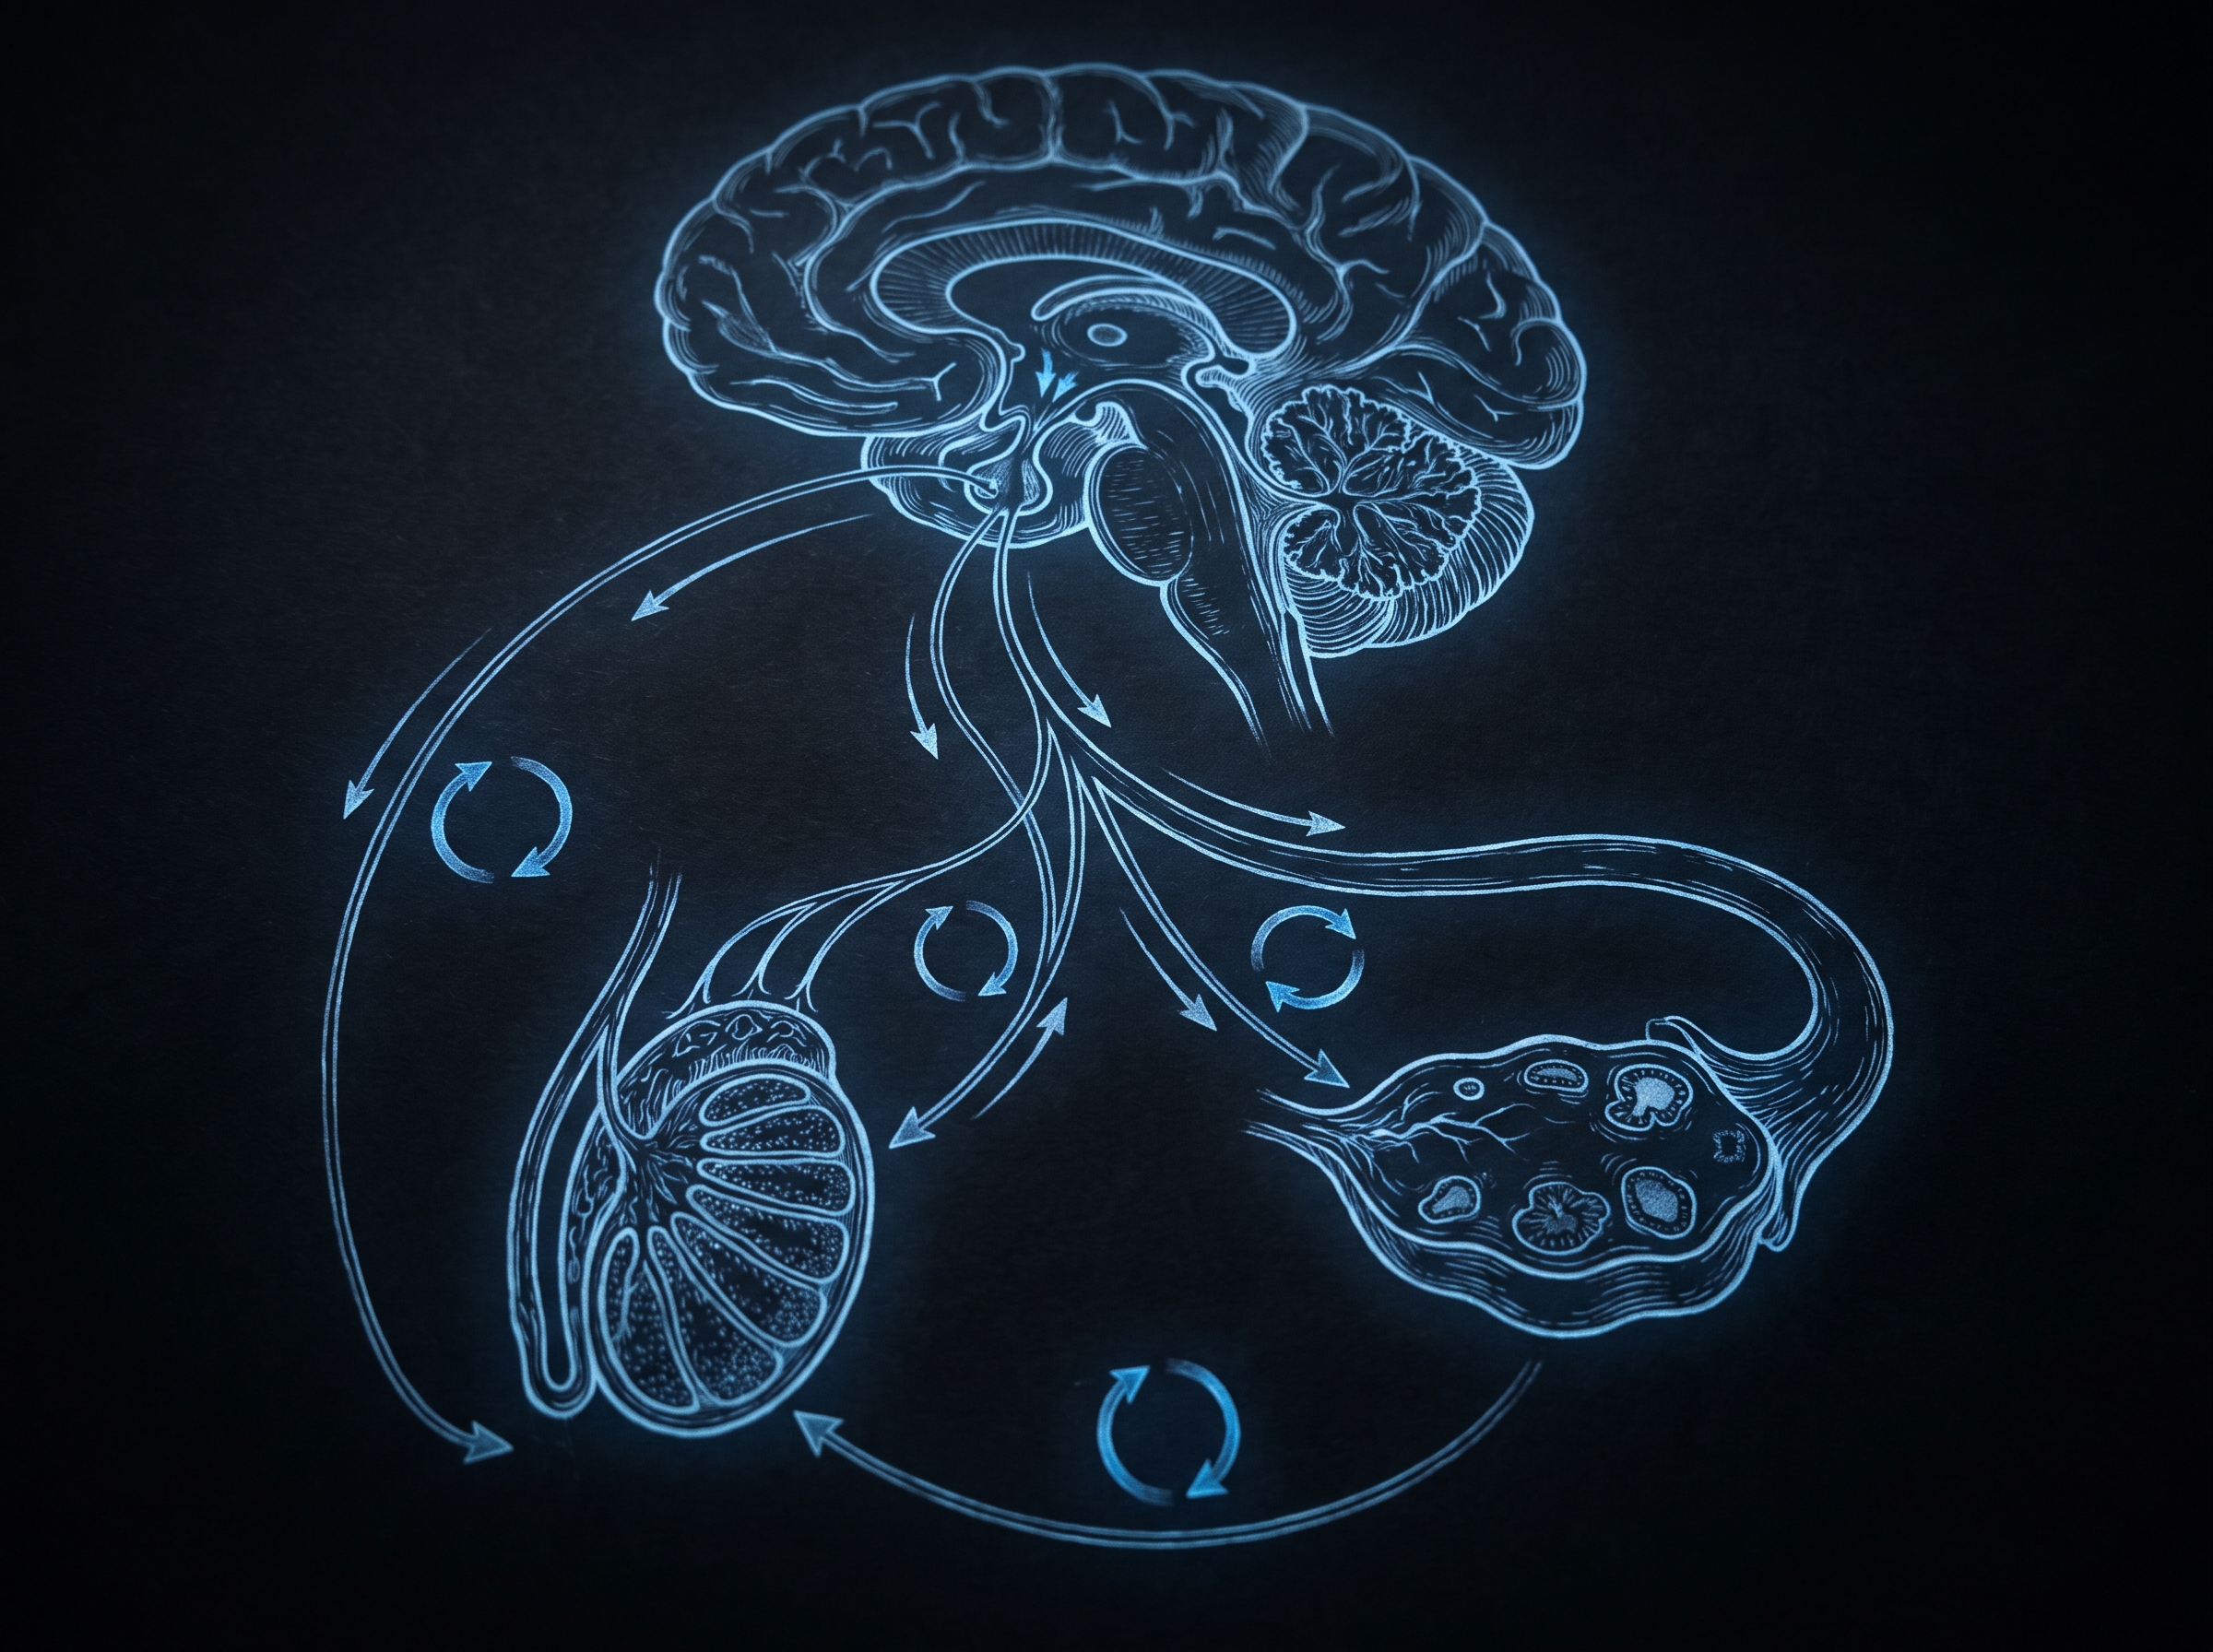
The hypothalamic-pituitary-gonadal (HPG) axis runs on a feedback loop. The hypothalamus pulses gonadotropin-releasing hormone (GnRH), which drives pituitary secretion of LH and FSH, which in turn stimulates Leydig cell testosterone production and Sertoli cell support for spermatogenesis. Intratesticular testosterone concentrations — the levels inside the testes themselves — run 50 to 100 times higher than serum levels and are absolutely required for sperm development [1].
When you inject or apply exogenous testosterone, circulating androgen levels rise quickly, and the hypothalamus interprets that signal as "enough — stop producing." GnRH pulses flatten. LH and FSH collapse. Leydig cell output drops. Intratesticular testosterone, which had been running at concentrations far above serum levels, crashes to values that cannot sustain spermatogenesis [1][5]. The testes do not stop working because they are broken; they stop because the central signal to produce has been withdrawn.
Male hormonal contraception trials quantify this suppression with uncomfortable precision. In one landmark study, weekly testosterone enanthate injections drove 65% of men to azoospermia within six months, with a mean time to azoospermia of approximately 120 days [8]. A broader review found that roughly 84% of men on exogenous testosterone reached sperm densities below 20 million/mL within a median of 3.7 months [1]. Those numbers are not edge cases — they are the central tendency of how the axis responds to exogenous androgens.
Recovery after stopping TRT is generally expected but not guaranteed. Studies estimate that 90% of men recover to at least 20 million sperm/mL within 12 months, and 96% within 16 months, but fewer than half return to their individual baseline sperm density [1][8]. For a man with already borderline semen parameters, that gap between "recovered to normal range" and "recovered to my personal baseline" can be the difference between conception and infertility. The Endocrine Society Clinical Practice Guidelines on male hypogonadism and the AUA guidelines on male infertility both classify active fertility desire as a contraindication to exogenous testosterone — not a caution, a contraindication [5][13].
For men exploring their options, the hormone optimization treatment hub provides a structured overview of the full range of evidence-based approaches, including TRT, SERMs, and gonadotropin protocols.
How Enclomiphene Works — and Why the Mechanism Matters
Enclomiphene citrate is the purified trans-isomer of clomiphene, a selective estrogen receptor modulator (SERM). Where exogenous testosterone bypasses the HPG axis entirely, enclomiphene works upstream of the testes. It antagonizes estrogen receptors at the hypothalamus and pituitary, reducing estrogen's negative feedback on GnRH secretion. The result: GnRH pulses increase, LH and FSH rise, Leydig cells receive a stronger signal, and intratesticular testosterone climbs — all through the man's own biology [4][14].
The clinical implications of that mechanistic difference are substantial. Because enclomiphene stimulates endogenous testosterone production rather than substituting for it, gonadotropin levels remain elevated rather than suppressed. FSH, which is the primary driver of Sertoli cell function and spermatogenesis, stays active or increases. Sperm production is maintained or improved, not killed off [10].
Clomiphene citrate, the racemic parent compound, has been used off-label in hypogonadal men for years with broadly similar results, though its regulatory approval in the United States is for ovulation induction in women. Enclomiphene — sometimes marketed as Androxal — was developed specifically to isolate the beneficial gonadotropin-stimulating properties of the trans-isomer while reducing the estrogen-agonist activity associated with zuclomiphene, the cis-isomer [4][15]. That pharmacological refinement may offer a cleaner hormonal profile, though the broader body of male SERM literature includes both compounds. For a deeper comparison of how these two hormone strategies play out in real clinical practice, see our editorial on testosterone vs. enclomiphene for men: which hormone strategy actually works in 2026.
It is worth noting what enclomiphene does not do: it does not work in primary hypogonadism, where the testes themselves are damaged and cannot respond to gonadotropin stimulation. For men with Klinefelter syndrome, testicular torsion history, or other primary testicular failure, the HPG axis is intact but the target organ is compromised. SERMs require functional testes to produce an effect. Careful diagnostic workup — including LH and FSH levels, which distinguish primary from secondary hypogonadism — is essential before selecting this pathway [5][6].
If you are evaluating online providers for SERM-based hormone therapy, PeterMD offers telehealth-based assessment and prescribing for men navigating this decision.
Head-to-Head: What the Clinical Trials Show
The most direct comparative data comes from Kaminetsky and colleagues, who conducted a randomized, open-label phase IIb study comparing enclomiphene citrate with topical testosterone gel in hypogonadal men [10][14]. The results were stark. Men receiving enclomiphene saw significant increases in serum testosterone, LH, and FSH. Every subject maintained sperm counts above 75 million/mL, with a mean sperm count of 176 million/mL [10]. Men receiving topical testosterone gel — a product category that includes formulations like AndroGel and Testim — achieved higher circulating testosterone levels but showed dramatic spermatogenic suppression: not one subject maintained sperm concentrations above 12 million/mL after three months of treatment [10][14].
A phase IIb double-blind, placebo-controlled study by Wiehle et al. enrolled 124 men with secondary hypogonadism and found that enclomiphene at 12.5 mg or 25 mg daily raised serum testosterone from baseline values around 210–217 ng/dL to approximately 406–472 ng/dL over three months, with concurrent increases in LH and FSH, while semen parameters were preserved [10]. A subsequent phase III study by Kim et al. in 265 overweight men aged 18–60 replicated these findings: enclomiphene normalized testosterone, FSH, and LH while maintaining sperm counts, while testosterone gel recipients showed hormonal normalization but spermatogenic suppression [10].
These trials target secondary hypogonadism specifically — men with low testosterone but low or inappropriately normal LH and FSH, indicating a central rather than testicular failure. That is also the population most likely to present to a men's health clinic with both hypogonadal symptoms and fertility concerns. The Bhasin et al. 2018 NEJM Testosterone Trials (TTrials), the large NIH-funded 7-arm study, did not enroll men with active fertility goals, but its documentation of testosterone's symptomatic benefits underscores why men want to stay on TRT even when it conflicts with reproductive plans — the energy, libido, and mood improvements are real and meaningful [5].
The practical tension this creates is genuine: enclomiphene may not produce the same magnitude of symptom relief that exogenous testosterone does, particularly in men with more severe hypogonadism. Some men find that their testosterone normalizes on enclomiphene but that subjective symptom improvement is incomplete. Whether that represents a pharmacological limitation or individual variability is not fully resolved in the current literature.
The Formulation Question: Does Any TRT Preserve Fertility?
This is a legitimate question, and the honest answer is: possibly, for one formulation, with significant caveats. Most exogenous testosterone preparations — including testosterone cypionate and enanthate injectables, transdermal gels, implantable pellets, and long-acting injectables like Aveed (testosterone undecanoate) — suppress spermatogenesis through the same HPG-axis mechanism described above [1][5][8]. Aveed carries an additional boxed warning for pulmonary oil microembolism (POME) and anaphylaxis, which does not reduce its spermatogenic suppression — it simply adds a separate safety concern [11].
Natesto, the intranasal testosterone gel administered three times daily, has attracted interest as a potentially less suppressive option because its short pharmacokinetic profile may allow LH and FSH to recover between doses. A 2026 open-label trial in 60 hypogonadal men found that 90.9% achieved normal testosterone levels, while a large majority preserved FSH and LH values, with 93.9% maintaining total motile sperm counts above 5 million at six months [19]. Those numbers are meaningfully better than what gel or injectable TRT produces. However, the study was small, open-label, and short-duration, and the AUA guidelines do not endorse any exogenous testosterone formulation for use in men seeking to preserve fertility [5]. Natesto may be worth discussing with a reproductive endocrinologist in specific clinical scenarios, but it should not be positioned as a fertility-safe alternative to enclomiphene based on current evidence.
The injectable testosterone Xyosted (testosterone enanthate subcutaneous) and standard intramuscular Depo-Testosterone both carry the same HPG-suppression liability as other injectables. If a man on any of these formulations wants to pursue conception, the clinical approach typically involves stopping TRT, initiating hCG to restore intratesticular testosterone, and sometimes adding a SERM. Recovery timelines vary — one analysis found average recovery times of 3.1 months after stopping injectables versus 7.4 months after stopping transdermal testosterone [8] — but individual variation is wide enough that planning around those averages is unreliable.
Tolerability, Side Effects, and Who Should Not Use Enclomiphene
Enclomiphene's side-effect profile differs from TRT's in character, not just magnitude. Because it works by blocking estrogenic negative feedback, some men experience estrogen-related symptoms — though the direction of that effect is more complex than it sounds. By raising LH and FSH, enclomiphene increases intratesticular testosterone production, which can also increase peripheral aromatization to estradiol. Men with elevated baseline aromatase activity or higher body fat may see estrogen climb alongside testosterone, potentially producing symptoms like mood fluctuation, water retention, or reduced sense of well-being.
The clinical trial literature on enclomiphene reports that tolerability is generally acceptable, but the experience is not uniform [10][15]. Some men report mood changes, cognitive fogginess, or a subjective sense of feeling "off" — symptoms that have been attributed to the compound's estrogenic and anti-estrogenic activity at different tissues. These effects are consistent with what is known about SERM pharmacology: estrogen receptor antagonism in the hypothalamus is the therapeutic goal, but estrogen receptor modulation in the brain and elsewhere can produce neuropsychological effects that vary by individual [15]. If these effects emerge, dose adjustment or switching to hCG-based gonadotropin therapy is the usual clinical response.
TRT carries its own tolerability liabilities. Erythrocytosis — elevated hematocrit — is among the most common, and the Endocrine Society Clinical Practice Guidelines on male hypogonadism recommend withdrawing or adjusting therapy when hematocrit exceeds 54% [5]. Prostate stimulation, potential cardiovascular effects, and acne are part of the standard informed-consent discussion. Men on exogenous testosterone also require regular monitoring of hematocrit, PSA, and testosterone levels in a way that enclomiphene does not demand to the same degree. The Journal of Clinical Endocrinology & Metabolism (JCEM) has published extensively on TRT monitoring parameters, reinforcing that these are not theoretical risks [5].
The broader HRT provider directory is a useful starting point for comparing telehealth and in-person options across both approaches.
For context on how testosterone therapy interacts with other quality-of-life markers, the piece on whether TRT improves sleep or makes it worse covers hormonal effects on sleep architecture that are relevant regardless of which protocol a man chooses. And if you want to understand how to distinguish genuine hypogonadism from normal age-related testosterone decline — a critical first diagnostic step before either therapy — this overview of low testosterone vs. normal aging walks through the workup systematically.

Making the Decision: A Framework for Fertility-Conscious Men
The decision between TRT and enclomiphene for a man with secondary hypogonadism and fertility goals is not genuinely close when fertility is the priority. Enclomiphene normalizes testosterone, preserves sperm production, and maintains the HPG axis in an active state — all outcomes that TRT works against by design [10][14]. The AUA/ASRM guideline on male infertility states plainly that clinicians should not prescribe exogenous testosterone to men interested in current or future fertility, and should instead use SERMs, aromatase inhibitors, hCG, or combinations thereof [13].
The practical framework breaks down as follows. For men with confirmed secondary hypogonadism who want to conceive within the next one to three years, enclomiphene (or clomiphene off-label) is the appropriate first-line testosterone-normalizing strategy. For men who are actively trying to conceive with documented oligozoospermia, hCG-based gonadotropin protocols — sometimes combined with FSH/HMG and a SERM — are the standard of care per reproductive endocrinology guidelines, not enclomiphene alone. For men who are currently on TRT and want to pursue fertility, the protocol involves stopping exogenous testosterone, initiating hCG to restore intratesticular testosterone, and waiting for spermatogenesis to recover — a process that can take 12 months or more with no guarantee of returning to individual baseline sperm density [1][5][8].
Where TRT remains appropriate is in men who have completed their families, men with primary hypogonadism where enclomiphene cannot work, or men who have tried SERM-based therapy and achieved inadequate symptomatic response after confirmed testosterone normalization. In those cases, the full range of TRT formulations — from weekly cypionate injections to long-acting Aveed to daily gels like AndroGel — is clinically appropriate, with formulation selection guided by patient preference, monitoring burden, and cost.
Men considering either path should also review their full hormonal picture: thyroid function, prolactin, and metabolic markers all intersect with testosterone levels in ways that can complicate both diagnosis and treatment selection. If you are curious about upstream lifestyle factors, the data on gut microbiome and testosterone are worth reviewing before committing to any pharmaceutical intervention.
The bottom line: for fertility-conscious men, enclomiphene is not just a preference — it is the mechanistically correct choice. TRT is not fertility-compatible in its standard forms, and the guidelines from the Endocrine Society, AUA, and EAU all agree. Every month on exogenous testosterone while trying to conceive is a month the axis is suppressed, sperm counts are declining, and the recovery clock has not yet started.
Frequently Asked Questions
Can I use TRT and still get my partner pregnant?
Conventional testosterone replacement therapy — including injectable forms like Depo-Testosterone, transdermal gels like AndroGel, and long-acting injectables like Aveed — suppresses sperm production in the majority of men, often to azoospermic levels within four to six months [1][8]. The AUA guideline on male infertility states that clinicians should not prescribe exogenous testosterone to men interested in current or future fertility [13]. While some men on TRT retain residual sperm counts sufficient for conception, this is unpredictable and not a strategy to plan around. If conception is the goal, stopping TRT and transitioning to a fertility-preserving protocol under reproductive endocrinology guidance is the appropriate course.
How long does it take to recover sperm production after stopping TRT?
Most men recover to sperm concentrations above 20 million/mL within 12 months of stopping exogenous testosterone, with approximately 96% recovering within 16 months [1][8]. However, recovery to an individual's personal pre-TRT baseline sperm density is less reliable — fewer than half of men in male contraception trials returned to their individual starting counts. Men who stopped injectable testosterone recovered spermatogenesis faster on average (approximately 3.1 months) than those stopping transdermal testosterone (approximately 7.4 months), though individual variation is substantial [8]. Physicians often accelerate recovery by adding hCG after TRT cessation to restore intratesticular testosterone signaling.
Is enclomiphene FDA-approved for male hypogonadism?
As of October 2026, enclomiphene citrate (Androxal) has not received FDA approval for male secondary hypogonadism, despite completing phase III clinical trials demonstrating testosterone normalization and preservation of semen parameters [10]. Clomiphene citrate (Clomid) is similarly used off-label in men; its approved indication remains ovulation induction in women. Prescribing SERMs off-label for male hypogonadism is common practice among urologists and reproductive endocrinologists, and the AUA/ASRM infertility guidelines explicitly recommend SERMs as preferred over exogenous testosterone in men who desire fertility [13]. Patients should confirm with their prescribing physician that the off-label use is documented and that monitoring is in place.
Does enclomiphene work as well as TRT for hypogonadal symptoms?
Enclomiphene normalizes serum testosterone in men with secondary hypogonadism — phase IIb studies show increases from roughly 210 ng/dL to 406–472 ng/dL over three months [10] — and most men with secondary hypogonadism experience meaningful improvement in energy, libido, and mood. However, the symptomatic response may be less robust than with exogenous testosterone in men with more severe deficiency, and some men report incomplete resolution of fatigue or cognitive symptoms. The Bhasin et al. 2018 NEJM Testosterone Trials documented strong symptom improvements with exogenous testosterone specifically, and that data cannot be directly extrapolated to enclomiphene. For men prioritizing fertility, the spermatogenic advantage of enclomiphene outweighs the potential symptomatic gap. For men who have completed their families and need reliable symptom control, exogenous testosterone remains a well-supported option.
What happens if enclomiphene stops working or causes intolerable side effects?
If enclomiphene produces inadequate testosterone normalization or significant side effects — such as mood instability or estrogenic symptoms — the clinical alternatives for fertility-conscious men include hCG monotherapy, FSH/hCG combination protocols, or aromatase inhibitors, depending on the hormonal workup [4][13]. These approaches also preserve the HPG axis and spermatogenesis. Men who have confirmed azoospermia and want to conceive are typically managed by a reproductive urologist or reproductive endocrinologist rather than a general men's health provider, as the protocols become more complex. If fertility is no longer a concern, transitioning to standard TRT with a formulation matched to the patient's lifestyle and monitoring tolerance is appropriate at that point.
Sources
[1] PMC — Testosterone and Male Fertility
[4] PMC — SERMs for Male Hypogonadism and Fertility Preservation
[5] PMC — TRT and Fertility: Contemporary Review
[6] EAU Guidelines — Sexual and Reproductive Health: Male Hypogonadism
[8] Translational Andrology and Urology — TRT Recovery and Spermatogenesis
[10] PMC — Enclomiphene vs. Testosterone Gel: Clinical Trials
[11] FDA — Aveed (Testosterone Undecanoate) Prescribing Information 2025
[13] AUA — Guideline on Male Infertility
[14] PMC — Enclomiphene Citrate in Male Hypogonadism
Alpha Health Finder Editorial Team
Editorial Team
The Alpha Health Finder editorial team researches and writes evidence-based men's health content. Articles are grounded in cited primary sources and reviewed against a fixed editorial standard before publication. We are a research and directory team — not your prescribing clinicians.
Tools and references for this topic
Free calculators and reference charts built from the same sources as this article.
- ComparisonTRT vs Enclomiphene — An Approved Drug Against an Unapproved One
- ComparisonTRT vs hCG — Two Approved Drugs, One Shared Indication
- CalculatorTRT Cost Calculator — Cost Per Month, With and Without Insurance
- CostsTRT Cost Without Insurance: What the Drug Actually Costs
- ComparisonEnclomiphene vs Clomiphene: One Is Half of the Other
Looking for an online provider?
Find a qualified online provider — compare options vetted and reviewed by Alpha Health Finder.



